Private equity has been circling physician practices for years, but cardiology – long considered too complex, too capital-intensive, and too dependent on hospital relationships – has finally become the sector’s next major target. The deals are quiet, the terms are rarely disclosed, and the doctors signing on are often doing so with far more urgency than they let on.
Why Cardiology, Why Now
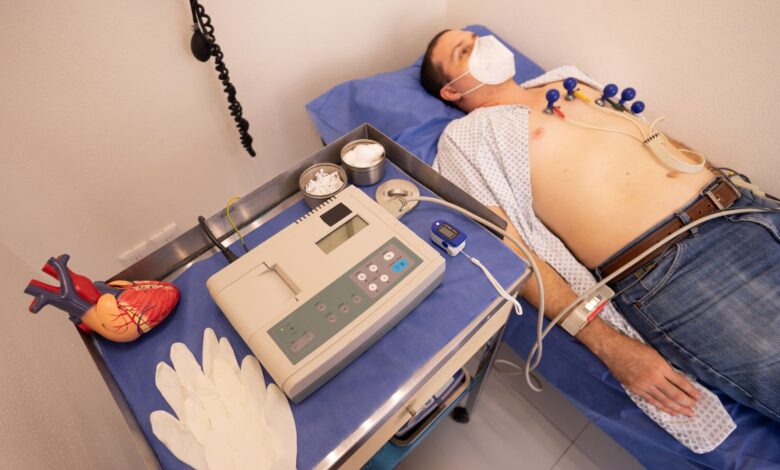
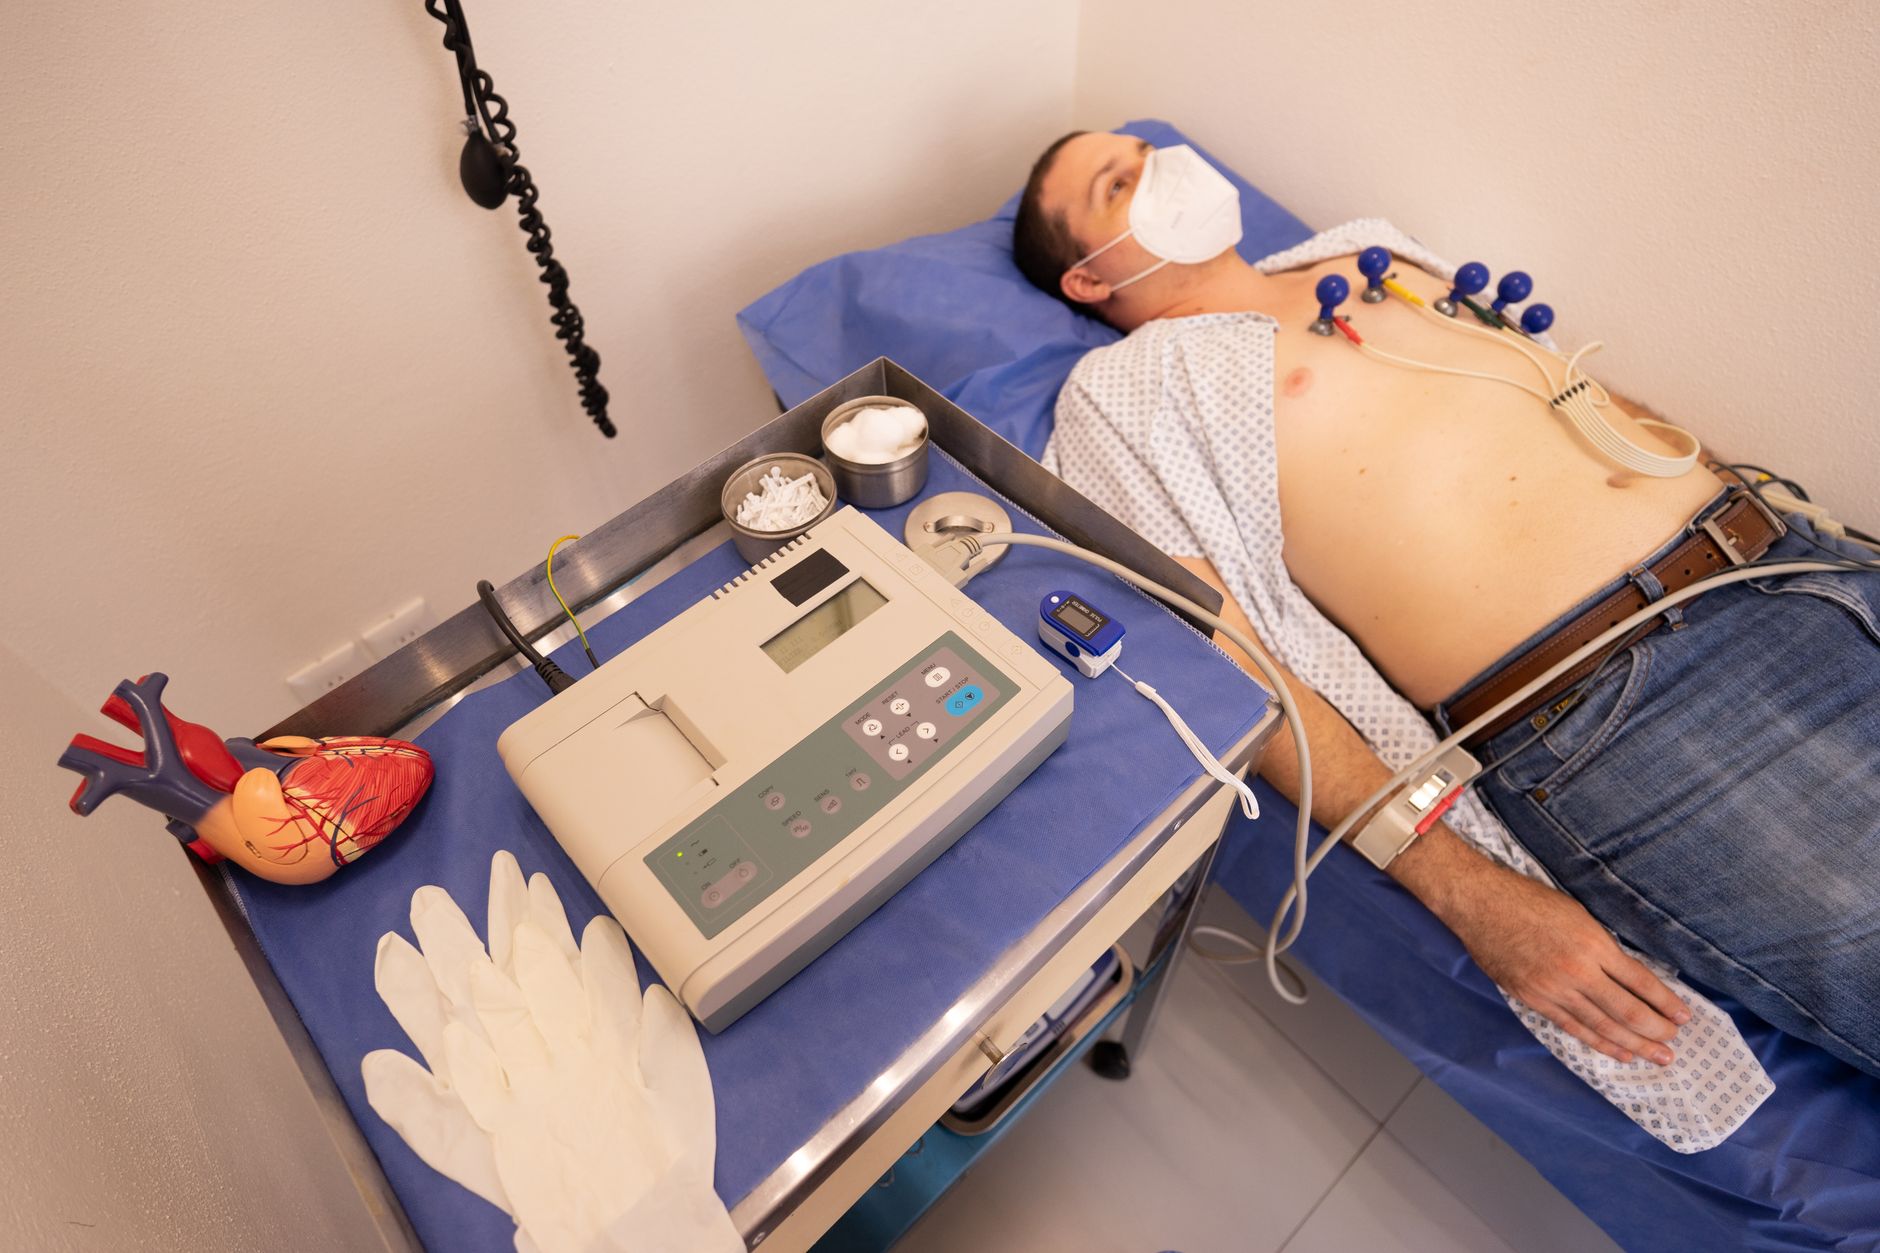
Cardiology sits at a particular intersection of volume and revenue that makes it attractive in ways that, say, primary care never quite was. Cardiologists perform high-reimbursement procedures – stress tests, echocardiograms, cardiac catheterizations, electrophysiology studies – that generate consistent, predictable income streams. When private equity builds a rollup, it needs practices that can sustain cash flow while the platform scales. Cardiology delivers that more reliably than most specialties.
There is also a supply-side pressure pushing independent cardiologists toward the exit. The administrative burden of running a regional cardiology group has grown considerably over the past decade. Prior authorization requirements from insurers have multiplied. Electronic health record compliance costs money and staff time. Recruiting younger cardiologists who want employment contracts rather than equity partnerships has become harder for practices that cannot offer the signing bonuses and salary guarantees that large hospital systems can. For a three- or four-physician group in a mid-sized metro area, the math of staying independent increasingly does not work.
Private equity buyers are stepping into that gap with offers that look generous on the surface – typically structured as a combination of upfront cash, equity in the new management company, and earnout provisions tied to performance targets over several years. The cardiologist selling at 60 gets liquidity. The 45-year-old partner gets a minority stake in something that might, theoretically, be worth more when the platform sells again in five to seven years. That second bite of the apple is a recurring sales pitch in these conversations, and it works.
The rollup strategy itself is straightforward. A PE sponsor acquires an anchor practice – usually a larger group with strong market share and established referral pipelines – then systematically adds smaller regional groups around it. Each acquisition expands geographic reach, adds procedural volume, and increases the platform’s negotiating leverage with commercial insurers. At scale, a cardiology group that controls a significant share of procedures in a region can demand better reimbursement rates than any individual practice could achieve alone. That spread between what the platform negotiates and what it costs to deliver care is where the return gets built.

The Tension Beneath the Transaction
What makes these deals more complicated than a standard business acquisition is that cardiology is not a widget business. The people selling their practices are also the people delivering care to patients with heart failure, arrhythmias, and post-surgical complications. When financial incentives and clinical decisions occupy the same space, the potential for conflict is real – and the history of PE involvement in other medical specialties offers some cautionary context.
The pattern seen in radiology consolidation is instructive: once a platform reaches sufficient scale, pressure to optimize throughput tends to intensify. Read rates go up, turnaround times get tracked, and the metrics that matter to the financial sponsor begin to crowd out the ones that matter to the clinician. Cardiologists operating inside PE-backed platforms will face versions of that same dynamic – more patients per day, tighter scheduling windows, performance dashboards that measure revenue per encounter alongside clinical outcomes.
Physician employment agreements inside these structures typically include non-compete clauses covering geographic areas large enough to make departure genuinely difficult. A cardiologist who sells their practice, receives their upfront payment, and then decides three years later that the clinical environment is untenable may find that they cannot practice within a radius that covers their entire patient base. The leverage in these negotiations sits almost entirely with the buyer, and many selling physicians – particularly those without M&A legal counsel experienced in healthcare transactions – do not fully appreciate what they are agreeing to until after the deal closes.
State-level corporate practice of medicine laws theoretically limit how much control a PE-backed management company can exert over clinical decisions. In practice, those limits are engineered around through management services organizations – legal structures that technically keep the physician group separate while giving the PE platform contractual control over billing, staffing, scheduling, supply purchasing, and capital allocation. The physician nominally runs the clinical operation. The management company runs everything else. The distinction matters legally but often dissolves practically.
Patients, for their part, rarely know any of this has happened. A cardiology group that operates under the same name, in the same office, with the same physicians after a PE acquisition looks identical from the outside. The ownership change is disclosed in regulatory filings that no patient will ever read. Whether that invisibility is a feature or a problem depends entirely on how the new owners choose to operate the business.
Where This Consolidation Wave Is Heading
The cardiology rollup market is still early relative to what happened in emergency medicine, anesthesiology, and dermatology – specialties that are now dominated by a small number of PE-backed platforms after years of aggressive consolidation. Cardiology’s complexity slowed the timeline, but the infrastructure for large-scale rollups is now in place, and several well-capitalized sponsors are actively building platforms. The independent regional cardiology group that feels insulated by its hospital relationships and local reputation may find that insulation eroding faster than expected as competitors inside PE platforms begin offering recruitment packages and technology investments that independent groups simply cannot match.
The cardiologists most likely to resist are those with genuine hospital employment as an alternative – physicians who can walk into a health system deal and trade independence for stability without going through a PE intermediary. For everyone else, the choice is increasingly between selling now at current valuations or waiting to see whether those valuations hold as the market matures. PE sponsors know that urgency benefits them, which is why the pitch to regional cardiology groups so often includes a quiet suggestion that the window for favorable terms is narrower than it appears.